Heart disease risk often develops before chest pain, breathlessness, or an abnormal test appears. You will be able to identify the measurements that matter, choose additional tests for a clear reason, and build a prevention plan that reflects your personal and family history.
Key takeaways
- Review blood pressure, cholesterol, diabetes, smoking and family history together.
- Use additional tests only when your risk profile gives them a clear purpose.
- Treat risk factors early with targeted changes and medical follow-up.
- Seek specialist input for abnormal results, strong family history or pregnancy-related complications.
What preventive cardiology looks for before symptoms appear
Preventive cardiology looks for early heart disease risk before chest pain, heart attack, stroke, or a procedure—not for proof that disease is already present. A cardiovascular risk assessment combines age, blood pressure, cholesterol, diabetes status, smoking, weight, physical activity, kidney function, sleep apnoea, family history, inflammatory disease, and pregnancy-related complications.
Routine evaluation is useful for:
- Asymptomatic adults aged 40–75, to identify modifiable risk before disease becomes apparent.
- People with diabetes, hypertension, chronic kidney disease, obesity, persistent triglycerides of at least 175 mg/dL, or inflammatory conditions such as rheumatoid arthritis or psoriasis.
- Current smokers and people whose first-degree relative had premature heart disease.
- People with preeclampsia, gestational diabetes, premature menopause, or a strong family pattern suggesting inherited cholesterol disease.
A 10-year risk score supports decisions about prevention but does not replace clinical judgment, particularly near age limits or with familial hypercholesterolaemia. A single elevated office blood-pressure reading needs confirmation with home or ambulatory monitoring before treatment in most asymptomatic adults.
Routine resting or exercise ECG screening is different: without symptoms or an abnormal examination, it can produce false positives and unnecessary procedures. Risk findings guide prevention; they do not diagnose blocked arteries.
The measurements that build a useful cardiovascular risk profile
Record blood pressure with a validated upper-arm cuff, not one office reading alone. For home readings, avoid exercise, caffeine, and smoking beforehand; rest quietly, support your arm, and repeat measurements. Confirm an elevated office result with home or ambulatory monitoring before diagnosing hypertension.
| Measurement or test | What it adds | Important detail |
|---|---|---|
| Blood pressure | Estimates pressure-related risk | Wrist and finger devices are less reliable than validated upper-arm cuffs |
| Fasting lipid profile | Measures LDL cholesterol, HDL cholesterol, and triglycerides | Useful when triglycerides require clarification or a baseline fasting result |
| Nonfasting lipid profile | Provides a convenient cholesterol assessment | Suitable for many routine assessments |
| HbA1c and fasting glucose | Detect diabetes or prediabetes | Review both when results are borderline, discordant, or diabetes is suspected |
| Lipoprotein(a) | Identifies inherited risk missed by a standard panel | Measure at least once; ≥50 mg/dL (125 nmol/L) is risk-enhancing |
| Apolipoprotein B | Estimates the number of atherogenic particles | ≥130 mg/dL is risk-enhancing, especially with high triglycerides, metabolic syndrome, or diabetes |
Ask about age, smoking or vaping, physical activity, weight change, kidney disease, sleep apnoea, inflammatory disease, and diabetes or hypertension. Record premature heart disease or stroke in a first-degree relative, plus pregnancy complications such as pre-eclampsia or gestational diabetes.
For adults aged 40–75 without known ASCVD, combine a 10-year ASCVD estimate with these risk-enhancing factors; the calculator does not replace clinical judgment.
Choosing additional tests without confusing screening with diagnosis
A test that finds an abnormality is not automatically a useful screening test. In asymptomatic adults, routine ECG screening or exercise stress testing has not improved outcomes and can trigger false alarms, repeat imaging, invasive procedures, and anxiety.
| Test | When it adds value | Main trade-off |
|---|---|---|
| Resting ECG | Symptoms, an abnormal examination, fainting, palpitations, or a specific clinical indication | Incidental changes can lead to unnecessary testing |
| Exercise stress testing | Exertional chest discomfort or breathlessness when coronary disease is suspected and you can exercise | False positives; limited value for people without symptoms |
| Echocardiography | A murmur, abnormal ECG, heart-failure signs, valve suspicion, or known heart disease | No radiation, but incidental findings and follow-up costs can distract from risk-factor treatment |
| Coronary artery calcium score CT | A statin decision remains uncertain in an adult aged roughly 40–75 with LDL-C 70–189 mg/dL | Radiation and incidental findings; a score of 0 misses noncalcified plaque and does not erase smoking, diabetes, severe LDL elevation, or strong family history |
| CT coronary angiography | Symptoms require anatomical assessment of coronary narrowing | Contrast, radiation, motion artefacts, and incidental findings |
| Catheter angiography | Strong evidence of obstructive disease or a need to plan treatment | Invasive; bleeding, kidney injury, contrast reactions, and artery complications |
An LDL-C of at least 190 mg/dL usually warrants high-intensity statin treatment without a risk calculation, so calcium scoring should not delay action. Catheter angiography is diagnostic and treatment-planning care, not a preventive checkup.
How to interpret results and turn risk into prevention
A result matters when it changes your next decision. Read the numbers together rather than treating one favourable result as permission to ignore the others.
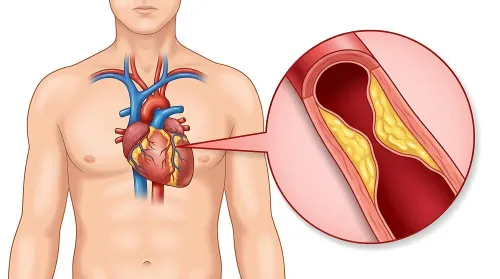
1. LDL cholesterol drives plaque formation. LDL-C of 190 mg/dL (4.9 mmol/L) or higher usually warrants high-intensity statin treatment without a risk calculation and assessment for familial hypercholesterolaemia; relatives may need screening. Lower levels still matter: reduce saturated fat, increase soluble fibre, exercise, and discuss medication when overall risk supports it.
2. HDL cholesterol is associated with risk, but a high HDL does not cancel high LDL or smoking. High triglycerides often point to excess alcohol, refined carbohydrates, obesity, diabetes, or metabolic syndrome; address these causes and recheck a fasting level when needed.
3. Persistent blood pressure of 130/80 mmHg or higher deserves confirmation with properly taken home readings. Reduce sodium, lose excess weight, exercise, moderate alcohol, and use prescribed treatment.
4. HbA1c below 5.7% is generally normal, 5.7%–6.4% indicates prediabetes, and 6.5% or higher indicates diabetes when confirmed. Weight management, activity, and diabetes care reduce vascular risk.
5. For adults aged 40–75 without ASCVD, use the 10-year ASCVD risk estimate with clinical judgment. At 10% or higher, discuss a statin; at 7.5%–under 10%, selective treatment is reasonable.
6. Measure Lp(a) at least once; an elevated inherited level strengthens the case for aggressive risk-factor control. ApoB of 130 mg/dL or higher signals excess atherogenic particles, especially with high triglycerides or diabetes.
Do not start aspirin routinely: bleeding can outweigh benefit, particularly from age 60. A CAC score of zero lowers near-term risk but does not erase smoking, diabetes, severe LDL elevation, or family-history risk.
Preparing for follow-up and knowing when specialist input matters
Bring your medication list, recent test results, home blood-pressure monitoring log, and questions about your next decision. Record each medicine’s dose, note missed doses, and write down symptoms with their timing, trigger, and duration.
- Use a validated upper-arm cuff, not a wrist or finger device. Avoid exercise, caffeine, and smoking for 30 minutes, sit quietly for five minutes, support your arm at heart level, and take two readings one minute apart at the same times each day.
- Share your family history of premature heart disease, including the relative’s age at diagnosis, plus smoking, diabetes, kidney disease, pregnancy complications, inflammatory conditions, and current activity level.
- Ask what requires confirmation. A single high office reading does not usually diagnose chronic hypertension; ambulatory monitoring or properly collected home readings can prevent an unnecessary treatment decision.
A cardiology consultation helps when risk factors conflict, cholesterol treatment remains uncertain, blood pressure stays high outside the clinic, or a family history of premature heart disease suggests inherited risk. It is also useful when you need to decide whether a test such as coronary calcium scoring adds information, rather than ordering tests indiscriminately.
Dr Vijay Bang Cardiologist in Mumbai can help separate preventive follow-up from testing for established disease.
Do not wait for a routine appointment for urgent heart symptoms:
- Chest pressure, squeezing, or pain lasting more than a few minutes
- Breathlessness at rest, fainting, or sudden severe weakness
- A fast or irregular heartbeat with dizziness or chest discomfort
- Sudden facial droop, arm weakness, or trouble speaking
Call emergency services immediately and do not drive yourself.
Related services
Coronary Angioplasty About Coronary Angioplasty and why you need the best angioplasty doctor The Percutaneous coronary angioplasty (PTCA or PCI) is a non-surgical... View service → |
Pacemaker Pacemaker Why do you need a pacemaker specialist Pacemakers are temporary or permanent, a medical device which uses electrical impulses, delivered by... |
Frequently asked questions
What does preventive cardiology look for before symptoms appear?
It looks for risk factors linked to future heart attack, stroke and cardiovascular disease, including high blood pressure, abnormal cholesterol, diabetes, smoking, kidney disease, family history and sleep apnoea.
Which measurements build a useful cardiovascular risk profile?
A useful profile combines age, blood pressure, cholesterol, diabetes status, smoking, weight, physical activity, kidney function, sleep apnoea, family history, inflammatory disease and pregnancy-related complications.
When are additional heart tests appropriate?
Additional tests should answer a specific clinical question. Screening estimates future risk, while diagnostic tests investigate symptoms, abnormal findings or suspected existing disease.
How should you respond to cardiovascular risk results?
Review the results with a clinician, identify changeable risks, set follow-up targets and use medication, lifestyle measures or further evaluation when indicated.
Related services
ECG (Electrocardiogram) An ECG (Electrocardiogram) is a simple, painless test that records the electrical activity of the heart. View service → |
Cardiology Cardiology The Cardiology is a branch of cardiac medicine dealing with diseases of the heart as well as parts of the blood circulatory system. |
Device Closure Vascular closure devices are cardiac devices used to achieve closure of the small hole in the artery after a cardiovascular procedure of endovascular... View service → |
TAVI / TAVR / PAVR Catheter based, transcatheter aortic valve replacement (TAVR), also known as transcatheter aortic valve implantation (TAVI). View service → |